Przejdź do treści

Seeing the Impact: How Realistic Pediatric Simulation Strengthens Clinical Judgment

Realism matters most when it helps learners recognize clinical cues, make decisions, take action, and understand the consequences of care. 

Why it matters

Meaningful pediatric simulation is not defined by appearance alone. It combines realistic assessment, immersion, responsive feedback, and structured debriefing to support clinical judgment and team learning.

Beyond realistic appearance

A patient monitor changes. Breath sounds shift. The chest begins to retract. A learner notices, reassesses, and changes course. 

In that moment, realism is doing more than making a pediatric simulation scenario look convincing. It is helping the learner connect observation, clinical judgment, action, and consequence.

That connection is especially important in pediatric care. Caring for children requires teams to recognize subtle changes, coordinate quickly, and deliver age-appropriate care with confidence. Simulation provides a safe environment in which to practice those moments before they happen with a real patient.  

A systematic review found that pediatric simulation-based education supports the development of decision-making, knowledge, attitudes, and skills.1 To understand how simulation produces these outcomes, it helps to look beyond appearance and consider the elements that make the experience clinically meaningful. 

What makes pediatric simulation realistic?

Realistic simulation is often associated with how a patient simulator looks. Physical fidelity can support engagement, but meaningful realism is broader. It includes the clinical cues learners can identify, the assessments they can perform, the decisions they can make, and the way the simulated patient responds.

For a respiratory scenario, realism may mean observing work of breathing, hearing relevant findings, and seeing physiology change. For a team-based emergency, realism may also include appropriate roles, equipment, workflow, communication, and time pressure. 

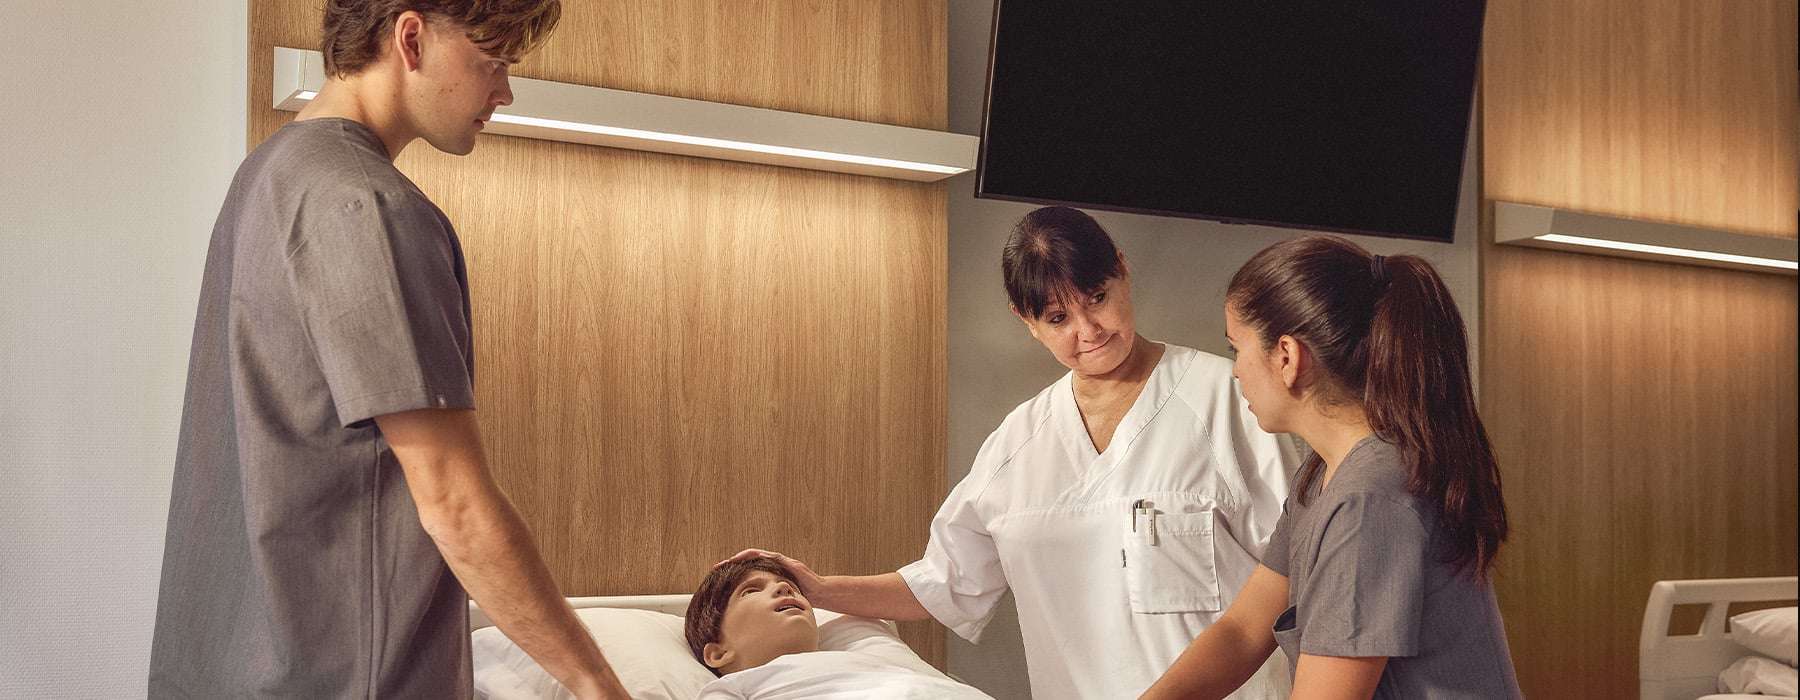
A team of nursing using SimJunior for training.

A useful question for educators:

What does this realism enable the learner or team to notice, decide, do, and discuss afterward?


A study of simulated pediatric dentistry scenarios found that students’ perception of clinical competence increased as their perception of overall scenario realism increased.2 The setting differs from acute pediatric care, but the study reinforces a useful design principle: participants experience realism across the complete scenario, not through one feature alone. 

Try this

Before reviewing simulator features, finish this sentence: “To meet this objective, learners must be able to…” Use the answer to decide which forms of realism matter.


Five questions to test whether realism supports learning 

  • Can learners identify clinically meaningful cues?
  • Can learners assess the patient naturally, without being coached around the simulator?
  • Can learners interpret findings and communicate their decisions?
  • Can the team perform interventions connected to the learning objective?
  • Does the simulated patient respond in a way that makes consequences visible? 

How simulation supports clinical judgment 

Clinical judgment is a sequence. Learners notice what matters, interpret what the information may mean, respond, and reflect on the result. Pediatric simulation can make that process visible and available for discussion.

When a scenario provides credible assessment findings, learners must decide which information is relevant. When the simulated patient changes in response to care, learners can examine whether their interpretation and intervention were appropriate. The learning comes from connecting a clinical skill to the patient’s condition and the wider situation.

In a 2024 study of undergraduate nursing students, participants rated a high-fidelity pediatric simulation series higher than acute-care pediatric clinical experience for learning and confidence in all measured categories except patient communication. The measured categories included assessment, clinical decision-making, communication, and safety.3

The findings reflect learner perceptions rather than patient outcomes, but they show the potential value of simulation when pediatric clinical exposure is inconsistent. 

Three nurses using a SimJunior manikin for training. One of them is an educator.

Make thinking visible

During debriefing, ask learners to name the cue that changed their working diagnosis or next action.

Why immersion matters in pediatric simulation

Immersion is not simply theatrical detail. It is the learner’s ability to stay engaged with the clinical problem rather than being pulled out of the experience by missing cues, unnatural workarounds, or inconsistent responses from the simulator.

A scenario does not need to reproduce every detail of clinical practice. It needs enough coherence for participants to behave as they would in the situation being rehearsed. When assessment flows naturally and the patient responds credibly, learners can devote more attention to prioritization, communication, and decision-making. 

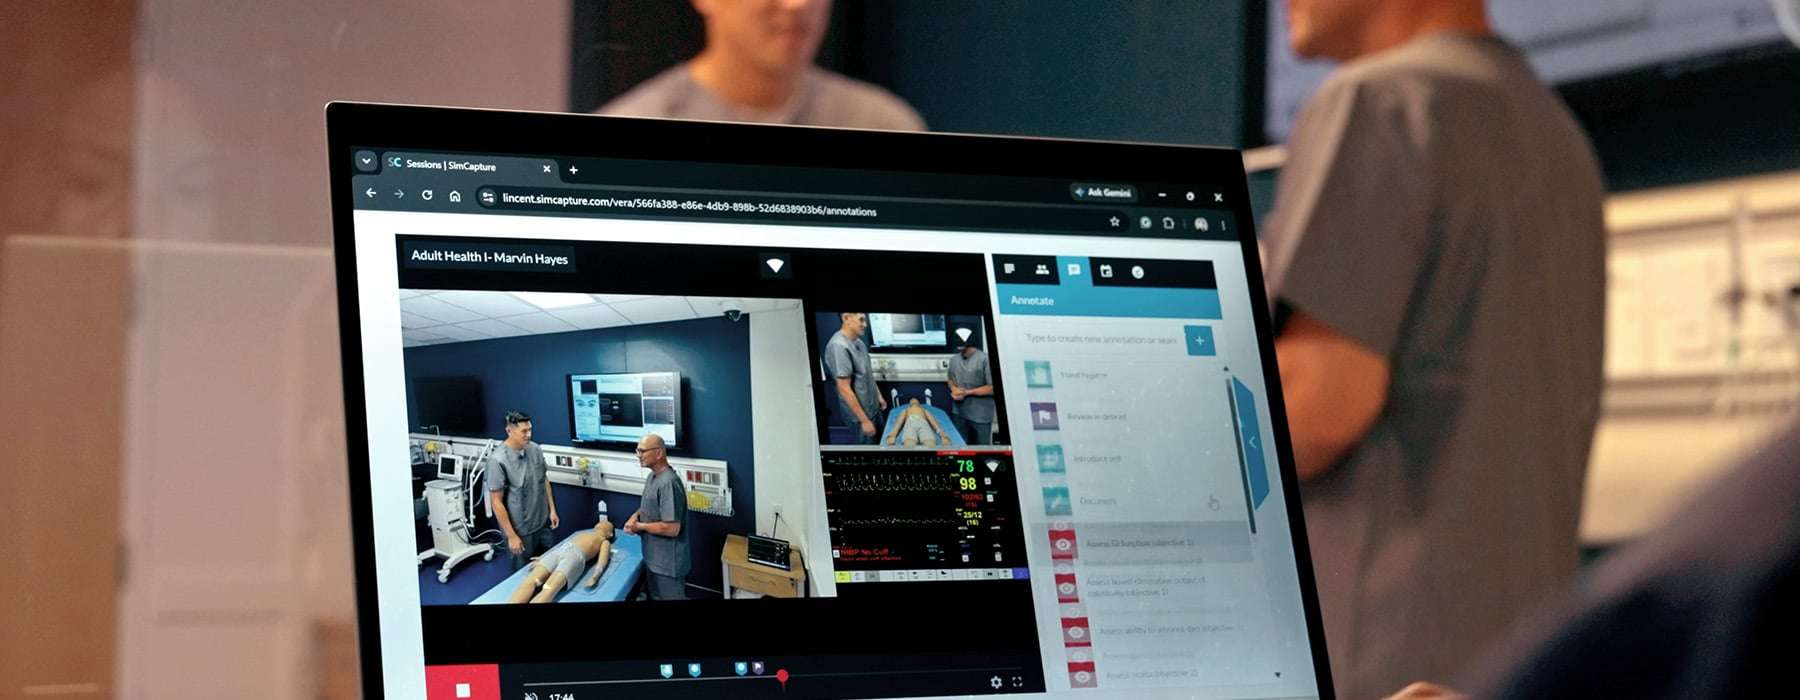
SimCapture in use on a screen, with SimJunior being used for simulation training.

Watch for friction

Record every moment when a facilitator must explain a limitation or tell learners to pretend. Identify which interruptions change assessment, decisions, communication, or workflow.

How feedback and debriefing turn activity into learning 

During a simulation scenario, feedback may appear as a change in the simulated patient. Vital signs may improve, respiratory effort may worsen, or clinical findings may shift after an intervention. After the scenario, structured debriefing helps participants examine what they noticed, why they acted, how the team worked, and what they would change.

The 2025 Healthcare Simulation Standards of Best Practice state that simulation-based experiences should include an intentional, structured debriefing process. The standard describes debriefing as a way to identify and address gaps in knowledge, skills, attitudes, and communication, develop insight, improve future performance, and support transfer of learning to practice.4

A longitudinal pediatric emergency medicine curriculum that combined debriefing with good judgment, rapid-cycle deliberate practice, and task training reported high perceived educational value and repeated opportunities to practice critical procedures.  

The authors concluded that the approach was feasible for addressing training gaps, while noting that further work was needed to quantify the reduction in those gaps.5

The simulation should not end when the scenario stops. Patient response, observation, performance information, and facilitated reflection work together to help learners understand the consequences of care. 

 

Three healthcare students are turned towards an instructor who is standing by a SimJunior manikin and pointing up towards a screen.

Close the loop

Ask three linked questions: What did you notice? What did you do because of it? What changed next?


How the new SimJunior® supports meaningful pediatric simulation

The new SimJunior is a high-fidelity pediatric simulator representing an approximately 8-year-old child and supporting training for school-age patients. Laerdal positions SimJunior as the anchor of a broader pediatric solution for hospitals, professional education, and pre-hospital providers.

SimJunior is designed to support the clinical work learners need to practice, rather than realism for its own sake. Its capabilities include: 

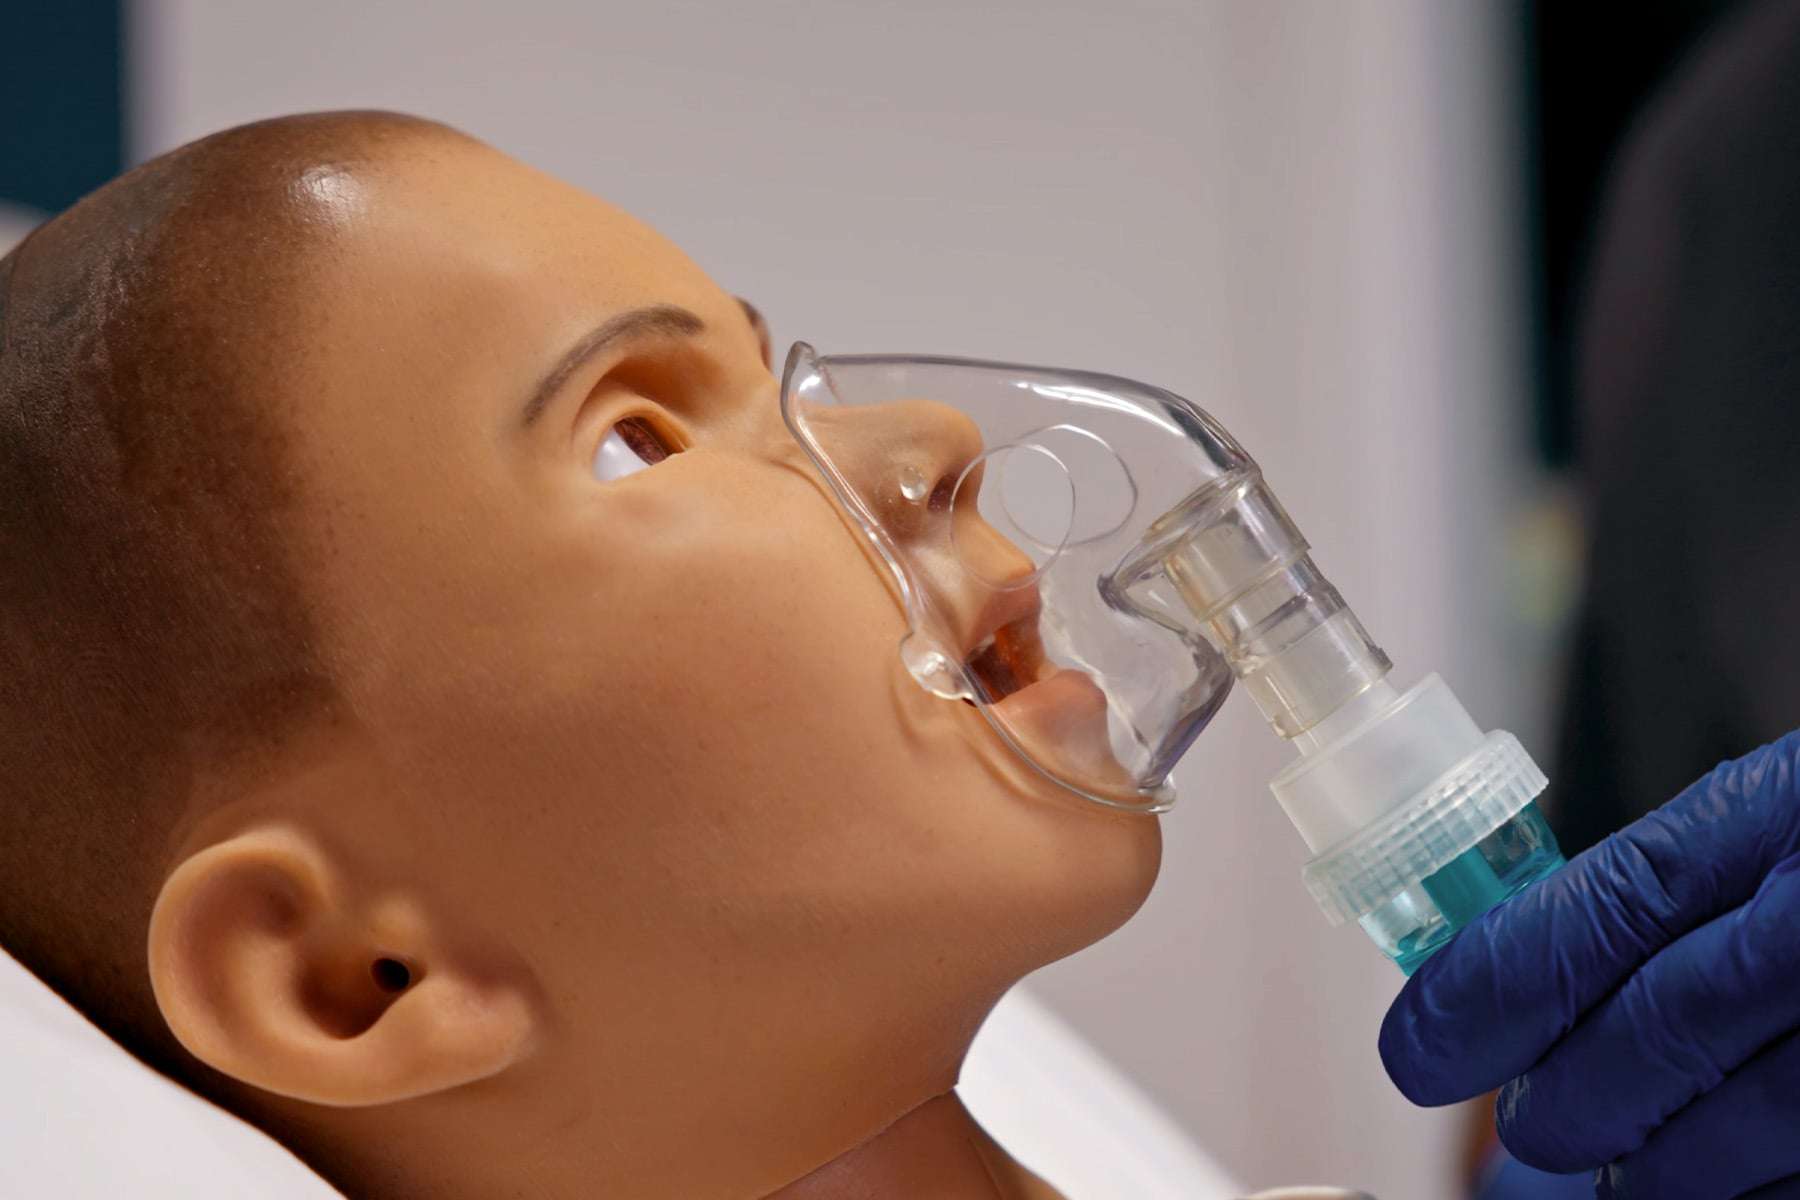
Closeup of SimJunior head. A resuscitator is placed over the manikin's nose and mouth.

Realistic work of breathing

Supports observation and reassessment of respiratory status. 

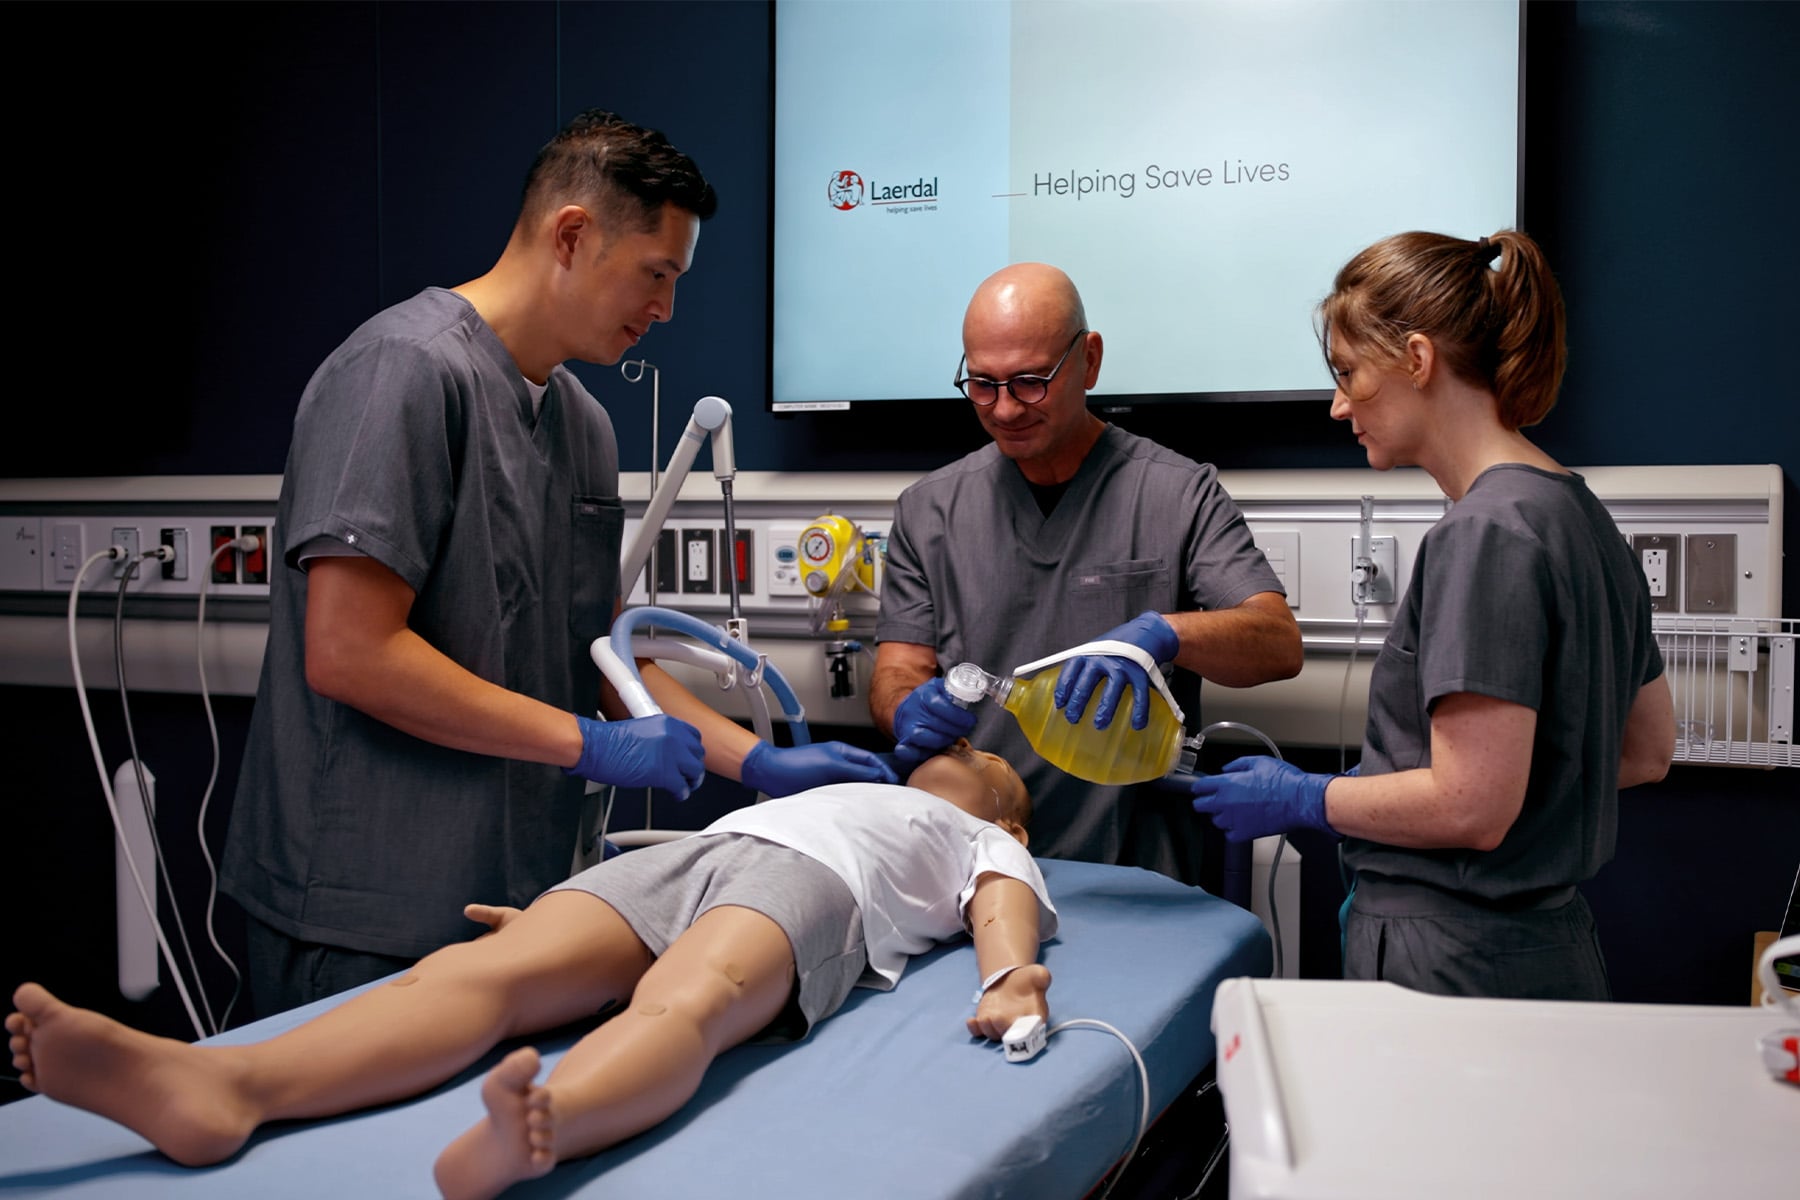
A team of nurses in a pediatric simulation training situation. An educator has placed a resuscitator over the mouth and nose of a SimJunior manikin, while nursing students observe.

Advanced airway capabilities 

Support assessment and intervention in airway-management scenarios.

An educator and two nursing students stand by a hospital bed with a SimJunior manikin. One of the students are flashing light into the eye of the patient simulator.

True bilateral functionality

Supports natural left-to-right and head-to-toe assessment without one-sided workarounds.

Two healthcare professionals using a stethoscope on a SimJunior manikin in a hospital environment.

Position-aware auscultation 

Supports listening in clinically relevant locations and interpreting findings.

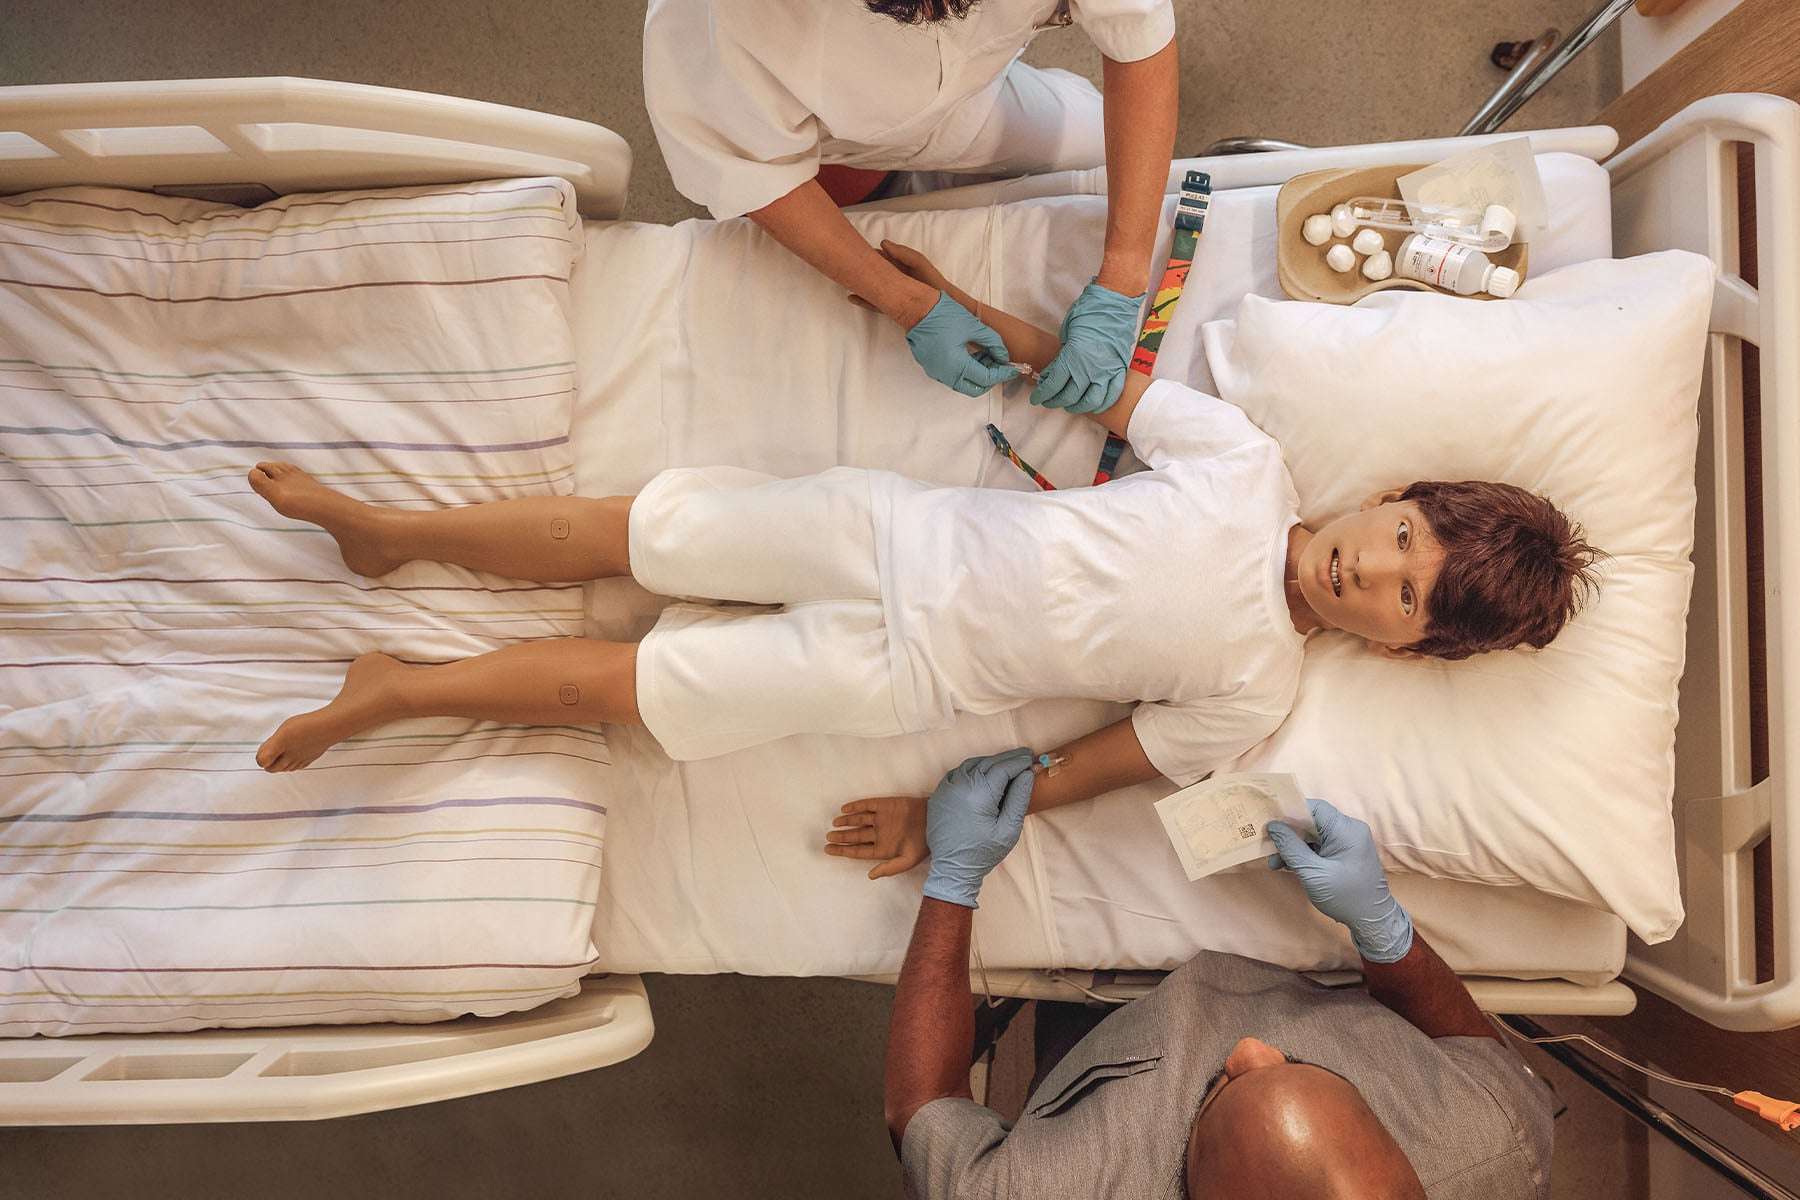
View from above of SimJunior on a hospital bed. Two healthcare workers standing on either side of the bed.

Fully articulated body

Supports patient handling and positioning during scenarios.

Close view of a screen where someone is using SimCapture. On the screen, and in the background, a team of nurses are performing simulation training on a SimJunior manikin.

Responsive patient and performance feedback

Helps connect decisions and actions with visible results and structured reflection.

Together, these capabilities are intended to make assessment and clinical workflow more credible and reduce the need for simulation workarounds.

Technology alone does not guarantee learning. Educational value still depends on clear objectives, well-designed scenarios, skilled facilitation, and structured debriefing. SimJunior can provide clinical possibilities and responsive cues. Educators determine how those possibilities are turned into practice, reflection, and improvement. 

Plan from the objective

Choose one judgment or team behavior first. Then select the SimJunior cues, interventions, responses, and debriefing evidence that make it observable.

How to design a realistic pediatric simulation scenario

Start with the clinical judgment or team behavior the experience should develop. Then work backward from the desired learning outcome.

  1. Define the decisions learners should make. 
  2. Identify the patient cues needed to support those decisions.
  3. Select interventions that allow participants to act on their assessment.
  4. Build responses that make the consequences of action or delay visible.
  5. Plan debriefing questions and evidence that will help participants reflect. 


Once the scenario is mapped, the next step is to assess whether those elements are working together as intended. Instead of treating realism as a feature checklist, use a short team assessment to ask:  

  • What can learners notice?
  • What decisions can they make?
  • What actions can they take?
  • And what patient response or debriefing evidence helps them learn from the result?

Seeing the impact

Realism changes what we can learn when it makes clinical thinking visible. It gives learners something credible to notice, a reason to decide, an opportunity to act, and evidence to reflect on afterward.

For pediatric educators and healthcare teams, that is the opportunity presented by the new SimJunior: not simply a more lifelike school-age patient, but a platform for assessment, immersion, intervention, feedback, and debriefing to work together. The goal is not to recreate reality perfectly. It is to create the conditions in which better judgment, stronger teamwork, and more meaningful practice can develop before a child needs care. 

A man in an orange t-shirt sitting by a hospital bed, holding a SimJunior manikin's hand. A nurse is watching from the other side of the bed.

Key takeaways

  • Realism should be judged by what it enables learners and teams to do. 
  • Assessment cues, responsive physiology, and natural workflows can support clinical judgment. 
  • Immersion helps keep attention on the patient and the clinical problem. 
  • Structured feedback and debriefing help participants connect performance with future improvement. 
  • SimJunior is designed to bring these elements together for school-age pediatric simulation. 

Frequently asked questions about pediatric simulation realism

What is realism in healthcare simulation?

Realism is the degree to which the patient, clinical cues, environment, workflow, and responses support the intended learning experience. It includes physical realism, but it is not limited to appearance. 

Does higher fidelity always create better learning?

Not automatically. Fidelity should be selected in relation to the learning objective. Clear objectives, scenario design, facilitation, and debriefing remain essential. 

Why is pediatric simulation important?

Pediatric simulation gives learners and teams opportunities to practice assessment, decision-making, procedures, communication, and teamwork in a safe learning environment, including situations that require rapid recognition, coordination, and age-appropriate care. 

How does feedback support clinical judgment?

Patient responses and structured debriefing help learners connect assessment and action with consequences, examine their reasoning, and identify changes for future performance. 

What is SimJunior®?

SimJunior is a high-fidelity pediatric simulator designed to support realistic, repeatable clinical training for school-age patient care across healthcare, professional education, and pre-hospital environments. 

Contact us about Pediatric Solutions

Państwa dane kontaktowe będą traktowane z należytą starannością, zgodnie z Polityką Prywatności Laerdal.

You may also like...

References

  1. Kim, E., Song, S., & Kim, S. (2023). Development of pediatric simulation-based education: A systematic review. BMC Nursing, 22, 291. https://doi.org/10.1186/s12912-023-01458-8
  2.  Bartolomé Villar, B., Real Benlloch, I., De la Hoz Calvo, A., & Coro-Montanet, G. (2022). Perception of realism and acquisition of clinical skills in simulated pediatric dentistry scenarios. International Journal of Environmental Research and Public Health, 19(18), 11387. https://doi.org/10.3390/ijerph191811387
  3. Cole, B. (2024). Enhancing clinical reasoning and student confidence through pediatric simulation. Journal of Pediatric Nursing, 78, e432-e437. https://doi.org/10.1016/j.pedn.2024.08.005
  4. INACSL Standards Committee et al. (2025). Healthcare Simulation Standards of Best Practice: The Debriefing Process. Clinical Simulation in Nursing, 105, 101775. https://www.nursingsimulation.org/article/S1876-1399(25)00092-1/fulltext
  5. Jeffers, J. M., & Poling, S. (2019). The development and implementation of a 12-month simulation-based learning curriculum for pediatric emergency medicine fellows utilizing debriefing with good judgment and rapid cycle deliberate practice. BMC Medical Education, 19, 22. https://doi.org/10.1186/s12909-018-1417-6