Saltar al contenido

Beyond Human Error: What Simulation Reveals About Healthcare Systems

At a glance 

When things go wrong, it is natural to focus first on an individual’s actions. The Institute of Medicine’s landmark report, To Err Is Human, emphasized the importance of looking beyond those actions to understand the systems and conditions that contribute to errors. By simulating real clinical scenarios, teams can observe how well-designed systems support performance—and how poorly designed ones set good people up to fail.

The blame instinct 

When a medical error occurs, it is not uncommon for people to ask:

“Who made the mistake?”

We look for the missed step, the delayed action, the wrong call. This reaction is natural—human beings want to pinpoint someone responsible. It gives us closure. It makes complex situations feel simpler.

But in healthcare, this instinct often leads us astray. Because most errors are not the result of bad people doing the wrong thing. In fact, it is a familiar quality improvement axiom that in most organizations, 85% of quality issues are not people related but rather systems related. They’re the result of good people trying to do the right thing in systems that make it hard.1


"A bad system will beat a good person every time."

W. Edwards Deming,

Quality Management Pioneer

The evidence is overwhelming 


Most errors are systemic 

The Institute of Medicine’s landmark 1999 report To Err Is Human found that the vast majority of adverse events in healthcare arise from system failures—not negligence or incompetence.

This includes: 

  • Poor communication
  • Lack of standardized processes
  • Workflow bottlenecks
  • Unreliable equipment
  • Inadequate staffing or supervision


These are not problems any single person can solve on their own.

This does not mean individuals are never responsible for errors. Clinical knowledge, technical skill, professionalism, and accountability remain essential to safe care. But modern patient safety recognizes that well-trained clinicians often work within systems that either support—or undermine—their ability to deliver safe care. Improving healthcare therefore requires both competent people and well-designed systems.


But why do we still focus on individuals?

  • Cultural legacy: Healthcare has long celebrated the achievements of individuals. Doctors, nurses, and others in healthcare are deservedly our heroes.
  • Legal and regulatory pressure: Chart reviews and investigations often demand a “root cause”—which often gets equated with a person. 
  • Cognitive bias: Individual actions are often easier to identify than the complex system factors that influence them. 

How simulation changes the conversation 

This is where translational simulation becomes so powerful.

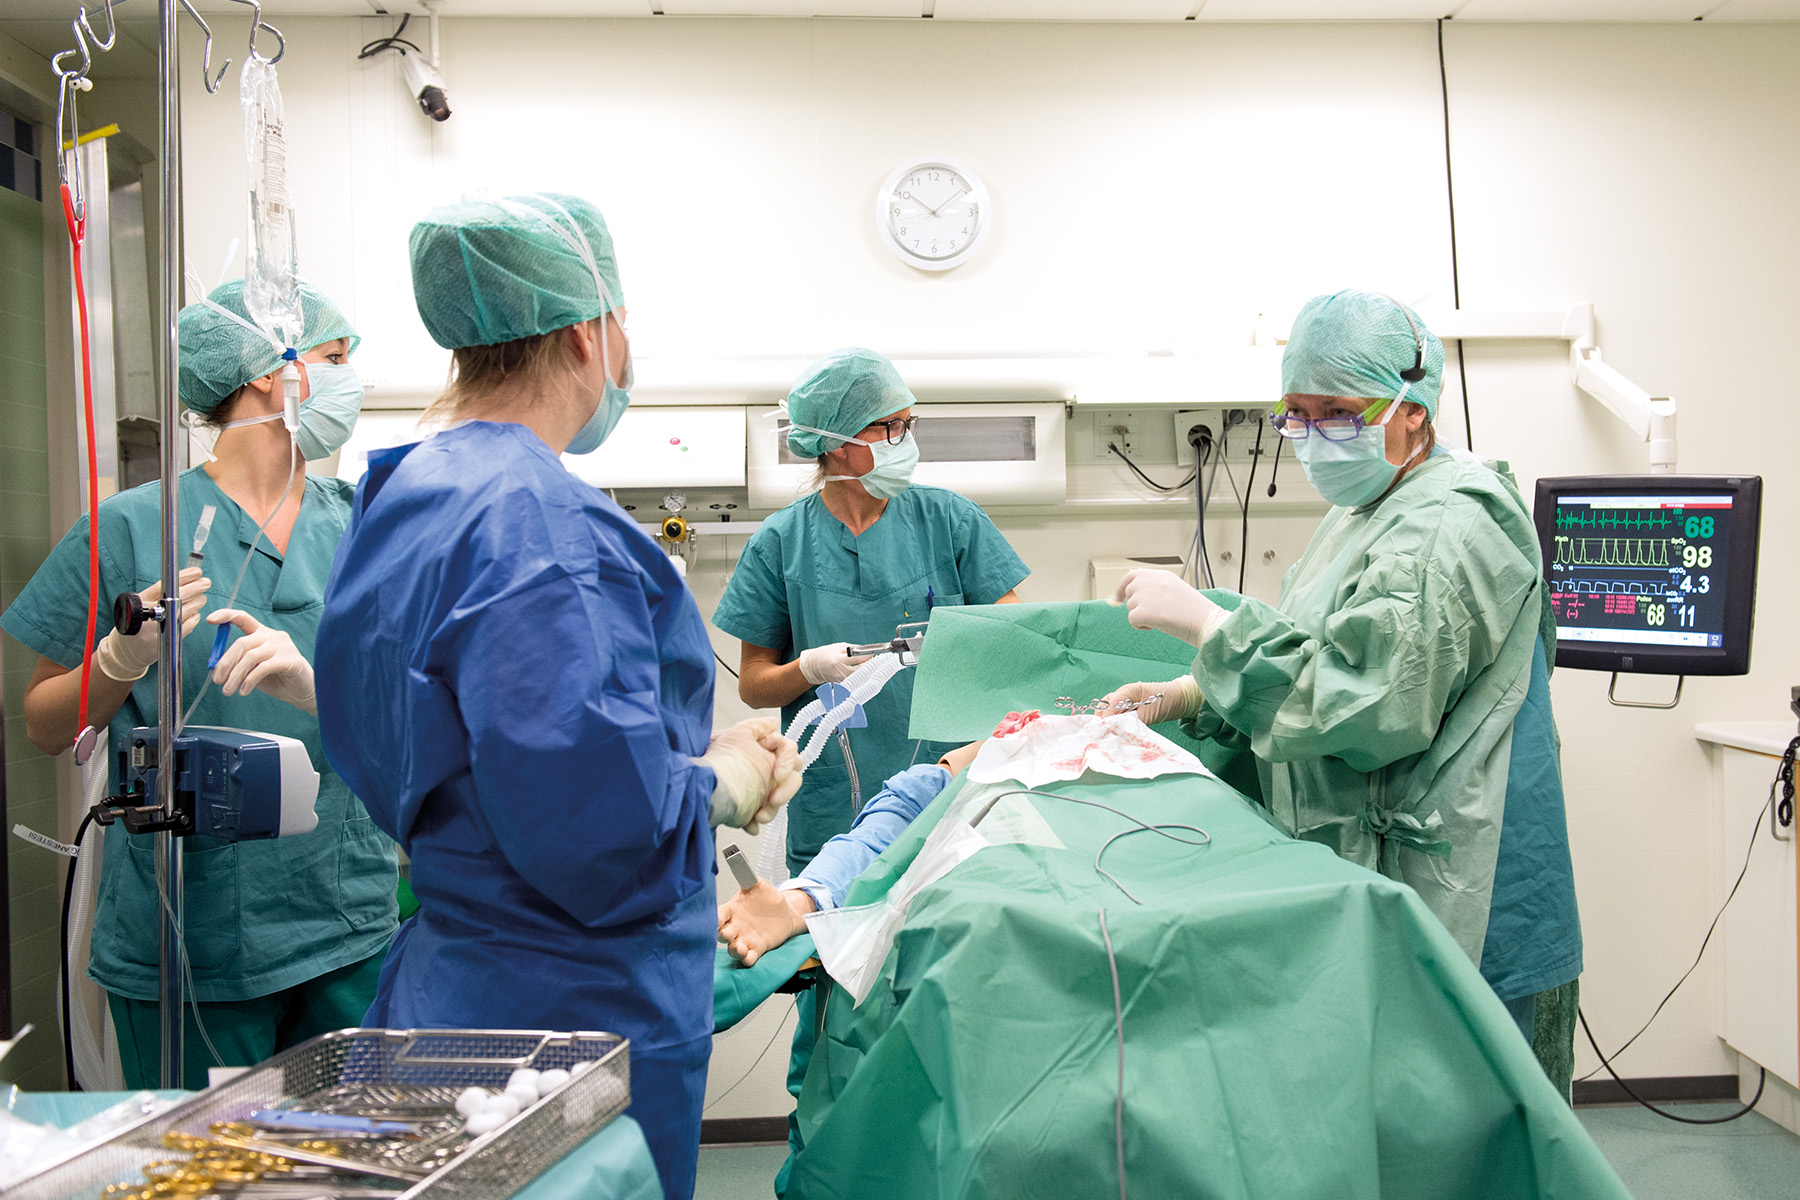
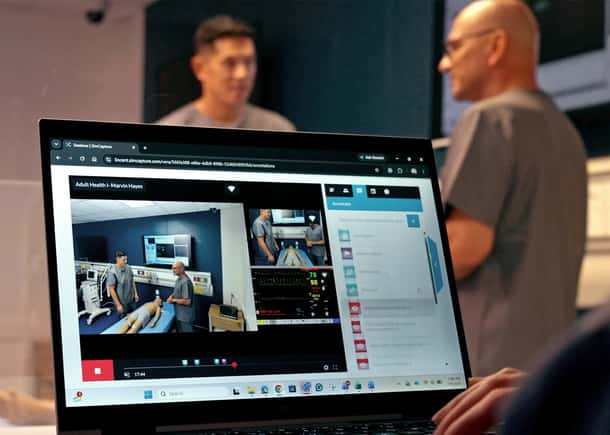
Unlike retrospective audits or chart reviews, simulation allows teams to watch systems in action—not on paper, but in real space, with real teams, under pressure. 


"In situ simulation [watching systems in action]... improves provider/team performance, identifies and mitigates threats to patient safety and improves systems and infrastructure."2

Dr. Andrew Petrosoniak MSc (Med Ed), FRCPC,

Emergency Physician and Trauma Team Leader at St. Michael’s Hospital in Toronto, Canada

Andrew Petrosoniak


Example 1: Preparing for postpartum hemorrhage before it happens 

Postpartum hemorrhage remains one of the leading causes of preventable maternal morbidity and mortality worldwide. Because these emergencies are both time-critical and multidisciplinary, many maternity units now use in situ simulation to test not only clinical skills, but also the systems that support rapid response. 

The Agency for Healthcare Research and Quality (AHRQ) has developed a postpartum hemorrhage simulation specifically to help labor and delivery teams evaluate how well their own systems perform under realistic conditions. Rather than measuring individual competency alone, the scenario encourages teams to test how quickly they can: 

  • Mobilize additional clinical support  
  • Access medications and blood products  
  • Use existing protocols and cognitive aids  
  • Communicate using structured handoffs such as SBAR  
  • Coordinate care across nursing, obstetric, anesthesia, and blood bank teams  


These exercises often uncover latent safety threats that are difficult to identify through chart reviews alone, such as delays in obtaining blood products, unclear escalation pathways, equipment access issues, or workflow bottlenecks. Those findings allow organizations to improve processes before a real patient experiences the same obstacles.  

Key takeaway: Simulation shifts the question from "Who made the mistake?" to "What in our system made timely care more difficult?"3


Example 2: Using simulation to design a safer trauma bay 

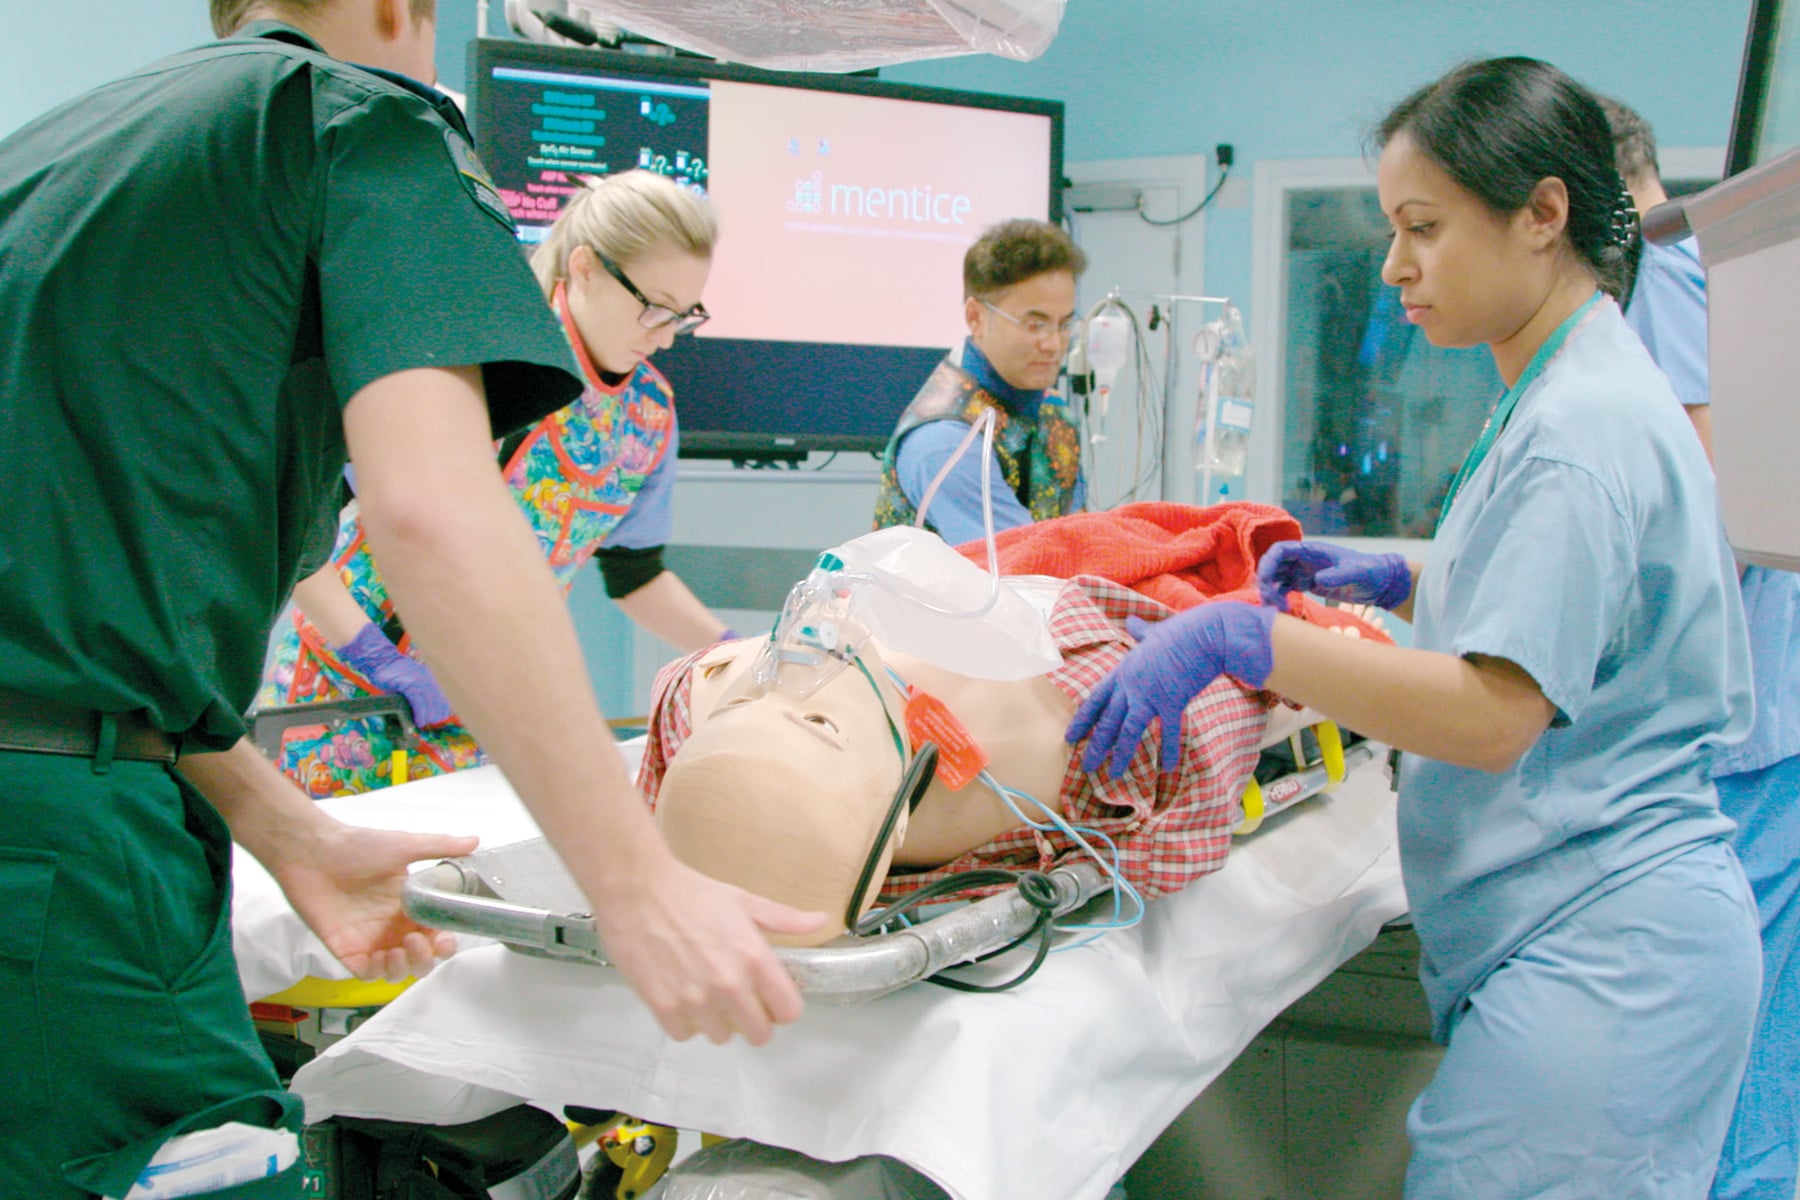
Before opening a newly constructed trauma bay at St. Michael's Hospital in Toronto, clinicians conducted a series of in situ simulations to test how the space would function during real trauma resuscitations. Rather than waiting for patients to reveal design flaws, the team used simulation to evaluate how people, equipment, and workflows interacted in the new environment.

The simulations uncovered numerous latent safety threats that were not apparent on architectural drawings alone, including: 

  • Patient monitors that became obstructed when doors were opened.  
  • IV poles and other equipment that interfered with stretcher movement.  
  • Critical supplies stored too far from the point of care.   
  • Workflow patterns that created unnecessary congestion around the patient.  


None of these issues reflected a lack of clinical knowledge or skill. Instead, they demonstrated how even a thoughtfully designed environment can unintentionally make safe care more difficult.

Because the problems were identified before the unit opened, the design team was able to relocate equipment, improve room layout, and optimize workflows before treating the first patient. 

Key takeaway: Simulation revealed risks that traditional design reviews could not, allowing the organization to improve the system before those hazards affected patient care.4

Why simulation makes system flaws visible 

Traditional Total Quality Management (TQM) methods that are more “industrial” in nature often focus on process maps and retrospective data. But these methods have blind spots: 

Traditional TQM method
What it sees
What it misses
Chart review What was documented  What actually happened
Root cause analysis Surface-level cause Deep system design issues
Policy updates Ideal workflow Real-time execution
Individual training Competency Context, pressure, resources


Simulation fills these gaps by: 

  • Reproducing care conditions
  • Revealing human-system interactions
  • Showing where design impedes care   
  • Allowing rapid testing and feedback 

A shift in mindset

To move from blame to systems thinking, we must change our debriefing questions:

From:

  • “Who should have done what differently?”

To:

  • “What about our system made this outcome more likely?”
  • “How could we make it easier to do the right thing next time?”
  • “Where did our tools, policies, or workflows fall short?”

When simulation becomes a system diagnostic tool, it shifts the focus from fixing people to fixing the environment people work in. 


"Simulation can become a testbed. It can become a place where the people who are actually doing the work get to explore it and get to offer ideas about how to make it better."5

Dr. Victoria Brazil,

Director, Bond Translational Simulation Collaborative; Professor of Emergency Medicine and Director of Simulation, Bond University

Victoria Brazil

Key priniciples for system-oriented simulation


1

Design scenarios based on real risks
Use actual near misses, high-risk handoffs, or planned protocol changes. 

2

Run simulations in-situ 
Real rooms, real workflows, real gear. No “perfect conditions.”

3

Debrief with a system lens
Use a structured systems framework to examine how people, tasks, tools, organizational factors, and the physical environment influence care.

4

Share responsibility across roles
Invite nurses, physicians, techs, and QI leaders to reflect together. 

5

Capture actionable system fixes
Use findings to drive change—not to file performance notes. 

The way forward


The problem is usually not the person. Simulation helps us see the system—and fix the parts that really matter.


Let us know how we can help you get started.

You may also like...

Contáctenos para hablar sobre la mejora de la calidad en el sector de la salud

Trataremos sus datos con cuidado de acuerdo con la Política de Privacidad de Laerdal.

References

  1. Best, M., & Neuhauser, D. (2005). W Edwards Deming: Father of quality management, patient and composer. Quality and Safety in Health Care, 14(4), 310–312. https://doi.org/10.1136/qshc.2005.015289 PubMed
  2. Petrosoniak, A., Auerbach, M., Wong, A. H., & Hicks, C. M. (2017). In situ simulation in emergency medicine: Moving beyond the simulation lab. Emergency Medicine Australasia, 29(1), 83–88. https://doi.org/10.1111/1742-6723.12705 PubMed
  3. Agency for Healthcare Research and Quality. (2023, July). Sample scenario for postpartum hemorrhage in situ simulation. https://www.ahrq.gov/patient-safety/settings/labor-delivery/perinatal-care/modules/situ/simulation-postpart-hemorrhage.html Agency for Healthcare Research and Quality
  4. Petrosoniak, A., Fan, M., Hicks, C. M., White, K., McGowan, M., Campbell, D., & Trbovich, P. (2021). Trauma Resuscitation Using in situ Simulation Team Training (TRUST) study: Latent safety threat evaluation using framework analysis and video review. BMJ Quality & Safety, 30(9), 739–746. https://doi.org/10.1136/bmjqs-2020-011363 PubMed
  5. Laerdal Medical. (n.d.). How can simulation drive quality improvement in your healthcare setting? https://laerdal.com/us/solutions/healthcare-quality-improvement/resources/how-can-simulation-drive-quality-improvement-in-your-healthcare-setting/